
IVF can be performed after tubal ligation because embryo transfer bypasses the fallopian tubes. Choosing between IVF and reversal depends on age, ovarian reserve, semen factors, tubal anatomy, surgical risk, desired family size, timeline, cost, and preferences. Neither option is best for every patient.
TL;DR: Both IVF and tubal reversal may be considered after tubal ligation. Comparative study results depend on patient selection and do not predict an individual outcome. A fertility specialist and, when appropriate, reproductive surgeon can compare the options.
Table of Contents
- IVF vs Tubal Reversal: Which One Actually Works Better?
- Who Is a Good Candidate for IVF After Tubal Ligation?
- What Do IVF Success Rates Actually Look Like After Ligation?
- How Much Does This Cost, and Will Insurance Help?
- What Should You Ask at Your First Fertility Consultation?
- How Life IVF Center Evaluates Patients After Tubal Ligation
- Why the “Just Get IVF” Advice Oversimplifies a Real Decision
- Ready to Get Your Own Numbers? Book a Consultation
- Sources
- FAQ
IVF vs Tubal Reversal: Which One Actually Works Better?
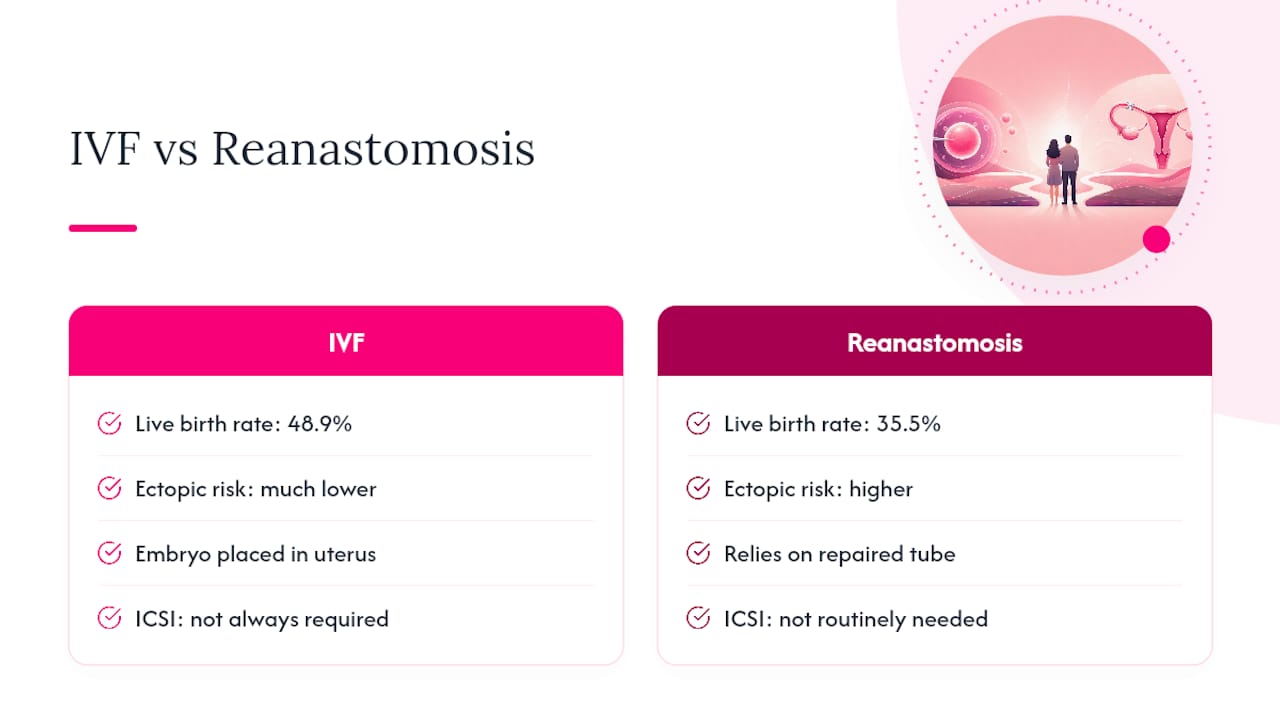
The clearest recent evidence comes from a 2026 comparative cohort that tracked outcomes for both paths. Live birth rates ran higher in the IVF group (48.9%) than in the tubal reanastomosis group (35.5%), and the ectopic pregnancy rate was dramatically lower with IVF than with reversal surgery.
Statistic callout: Women who conceive after tubal reanastomosis face roughly eight times the ectopic pregnancy rate seen in IVF pregnancies, largely because reconnected tubes can still trap an embryo before it reaches the uterus.
The trade-offs go beyond the headline numbers. IVF delivers a defined, per-cycle chance of pregnancy and a faster path to delivery for patients on a clock. Reversal offers something IVF cannot: the chance at natural conception, potentially more than once, without repeating a surgical or lab procedure for each pregnancy. That single advantage is why reversal still gets a fair hearing for the right candidate.
Each path carries its own risk profile:
- Tubal reversal: higher ectopic pregnancy risk, a multi-month recovery and conception window, and outcomes tied closely to the surgeon’s microsurgical experience.
- IVF: risk of ovarian hyperstimulation syndrome (OHSS) and a historical risk of multiple pregnancy, though transferring a single embryo largely controls that risk today.
- Both paths: outcomes drop as age increases and ovarian reserve declines, regardless of which procedure you choose.
Who Is a Good Candidate for IVF After Tubal Ligation?
Tubal ligation alone rarely disqualifies anyone from IVF. Because IVF sidesteps the fallopian tubes completely, the surgical history that prevents natural conception has almost no bearing on whether an egg can be fertilized in a lab and transferred to the uterus. Candidacy instead comes down to a short list of evaluations:
- Anti-Müllerian hormone (AMH) testing, which estimates ovarian reserve and helps predict how many eggs a stimulation cycle might yield.
- Antral follicle count, an ultrasound measure that adds detail to the AMH result.
- Semen analysis for a male partner or donor sperm plan, since sperm quality is one of the five factors the American Society for Reproductive Medicine flags as central to the decision.
- Uterine cavity assessment, confirming the uterus can support an embryo transfer.
- Medical history review, screening for conditions that need to be stabilized before stimulation medications begin.
A handful of situations call for caution: poorly controlled diabetes or thyroid disease, active cancer treatment, or serious cardiac conditions. None of these are automatic disqualifiers, but they usually mean your fertility team coordinates care with your other physicians before starting a cycle.
What Do IVF Success Rates Actually Look Like After Ligation?
Age is the dominant variable in every outcome figure that matters. Registry data consistently show IVF live birth rates decline as maternal age rises, which is why a 32 year old and a 42 year old with the same surgical history get very different counseling. Ovarian reserve, measured through AMH and antral follicle count, refines that picture further, since two women of the same age can have meaningfully different odds based on egg quantity alone.
The 2026 comparative cohort’s topline numbers, IVF’s 48.9% live birth rate against reanastomosis’s 35.5%, reflect a mixed-age sample rather than a guarantee for any individual. Your fertility team will translate that into a range specific to your labs and history.
Statistic callout: Ectopic pregnancy after IVF is much lower compared with after tubal reanastomosis, a gap driven by IVF placing the embryo directly in the uterine cavity instead of relying on a surgically repaired tube.
One common misconception: intracytoplasmic sperm injection (ICSI), where a single sperm is injected directly into an egg, is not automatically necessary for tubal-factor infertility. Evidence shows ICSI does not consistently improve pregnancy or live birth rates over conventional IVF when the only fertility issue is a prior ligation. It still makes sense when male-factor infertility or a history of fertilization failure is in the picture.
Preimplantation genetic testing for aneuploidy (PGT-A) comes up in some consultations, particularly for patients over 35 or with a history of pregnancy loss. It is worth discussing case by case rather than assuming it belongs in every protocol.
How Much Does This Cost, and Will Insurance Help?
Insurance coverage for fertility treatment after tubal ligation varies enormously by state, employer, and specific policy language, and the ASRM has noted that coverage gaps remain common even where general infertility benefits exist. Before assuming either path is covered, take a few concrete steps:
- Call the member services line on your insurance card and ask specifically whether “infertility treatment following voluntary sterilization” is covered, not just “infertility treatment” generally.
- Ask your employer’s benefits coordinator whether the plan defines infertility in a way that includes post-ligation patients.
- Confirm whether a referral or prior authorization is required before your first fertility consultation.
On the cost-effectiveness side, a decision-tree model comparing the two approaches found tubal anastomosis more cost-effective for most women under 41, while IVF became the more cost-effective option for women 41 and older, depending on assumptions about per-cycle IVF pricing. That crossover point is exactly why age-based counseling matters more than a blanket recommendation.
Pro Tip: Ask any clinic for a bundled, written cost estimate before you commit; separating “package price” from add-ons like genetic testing or extra storage months prevents budget surprises mid-cycle.
What Should You Ask at Your First Fertility Consultation?
Getting from “considering IVF” to “starting treatment” usually takes three steps.
- Book a fertility consultation that includes AMH testing, a semen analysis if applicable, and an ultrasound review of your tubal anatomy and uterine cavity.
- Review your results with your care team and discuss IVF versus reversal specifically in light of your age, goals, and how many children you hope to have.
- Choose a treatment path and request a written plan that spells out estimated cycles, timeline, and total cost before you start.
At that first visit, come prepared with questions that cut through generic reassurance:
- What is my estimated time to pregnancy with each option?
- How many IVF cycles should I budget for realistically?
- Is ICSI recommended for my case, or is conventional IVF sufficient?
- Would PGT-A add meaningful value given my age and history?
- If I choose reversal, how will ectopic pregnancy be monitored afterward?
- What does bundled pricing include, and what costs extra?
- What is my AMH and antral follicle count, in plain terms?
Pro Tip: A typical IVF cycle runs about two to three weeks from stimulation to transfer, while recovery from tubal reversal surgery plus the following months of attempted natural conception can stretch to six months or longer before you know whether it worked.
How Life IVF Center Evaluates Patients After Tubal Ligation
An evaluation may include ovarian reserve testing, semen analysis when applicable, and assessment of the uterus and surgical records. The findings can help determine whether IVF, consultation about reversal, or another approach is reasonable.
Beyond the clinical workup, patients receive personalized fertility care with support services including lab processing, pricing transparency, travel coordination, and staff assistance. We see this as a conversation, not a prescription. A consultation with our team is where your specific numbers, timeline, and goals turn into an actual plan.
Why the “Just Get IVF” Advice Oversimplifies a Real Decision
Ask around online and you’ll find a strong consensus that IVF is simply the better choice after tubal ligation, full stop. The data doesn’t fully support that as a blanket rule. The cost-effectiveness modeling is clear that tubal anastomosis holds up as the more economical choice for most women under 41, and reversal still offers something IVF structurally cannot: a shot at multiple natural pregnancies from a single procedure.

What the “just get IVF” crowd gets right is the risk math. An ectopic pregnancy rate near 16% after reversal, against roughly 2% with IVF, is a real clinical consideration, not a rounding error. For a patient with diminished ovarian reserve or limited time, that risk gap alone can settle the decision.
My honest read: the loudest voices on either side of this debate are usually generalizing from the case that fits their argument best. A 29 year old with excellent ovarian reserve and a skilled microsurgeon nearby is a genuinely different clinical picture than a 38 year old with a borderline AMH result. Both deserve individualized counseling, not a script. That’s also why I’d be skeptical of any clinic, including ours, that tries to sell you a path before running your actual numbers.
Ready to Get Your Own Numbers? Book a Consultation
You’ve read the research. Now the real question is what your AMH, your semen analysis, and your uterine cavity results actually say about your odds, and that only comes from testing, not from a blog post. Life IVF Center builds every plan around Precision IVF®, so your protocol reflects your biology and history instead of a generic template.
We offer treatment packages with published pricing, including the Advanced IVF Package at $13,500, so you can compare real costs before committing to a cycle. If you’re earlier in the process, pre-IVF testing like AMH review and semen analysis gets your baseline numbers on the table first. Book a consultation to walk through your results with our team and leave with a written plan and cost estimate, no guessing required.
Schedule your consultation and find out which path actually fits your biology.
This article is for general educational purposes and is not medical advice or a prediction of success. Discuss IVF, reversal, ectopic-pregnancy risk, costs, and alternatives with qualified professionals.
Sources
- Comparison of tubal reanastomosis and in vitro fertilisation for restoring fertility in women with a history of tubal ligation
- Role of tubal surgery in the era of assisted reproductive technology: a committee opinion (2021) | ASRM
FAQ
Will Insurance Pay for IVF After Tubal Ligation?
Coverage depends entirely on your specific plan and state, and it is never guaranteed. The ASRM notes that coverage for infertility treatment after voluntary sterilization varies widely, so call your insurer’s member services line and ask specifically about post-ligation fertility treatment before assuming anything.
What Is the Success Rate of IVF After Tubal Ligation?
Rates depend heavily on age and ovarian reserve rather than a single universal number. A 2026 comparative cohort found a 48.9% live birth rate with IVF versus 35.5% with tubal reanastomosis, though your individual odds depend on your own AMH and antral follicle count.
What Disqualifies You From Doing IVF?
Tubal ligation itself does not disqualify you from IVF, since the procedure bypasses the fallopian tubes entirely. Serious uncontrolled medical conditions, active cancer treatment, or a uterine cavity that cannot support a pregnancy are the more common reasons a cycle gets paused or restructured.
What Is the 120 Rule for Tubal Ligation?
There is no established clinical numeric rule recognized in reproductive medicine guidance for tubal ligation reversal or IVF candidacy. If you’ve seen this term elsewhere, ask your fertility team directly, since candidacy is based on age, ovarian reserve, and anatomy rather than a fixed numeric formula.
This article is for general educational purposes only and is not a substitute for personalized medical advice, diagnosis, or treatment. Fertility care is highly individual; please consult a qualified healthcare professional about your specific circumstances.
