
Donor genetic testing screens for carrier and chromosomal risks to reduce, but not eliminate, the chance of passing on many inherited conditions. Programs commonly run carrier screening or expanded carrier screening, karyotype analysis, and hemoglobinopathy testing on sperm donors. Because no panel covers every condition, intended parents should review the donor’s actual report and consult a genetics professional or their clinic to confirm that recipient testing matches what the donor was screened for.
TL;DR:
- Request the donor’s full report, gene list, testing method, and date; compare it with your results, since matching coverage matters more than gene count.
- A negative result lowers risk only for conditions and variants the panel detects; family history can still warrant targeted testing after a broad screen.
- If the donor is a carrier, test the recipient for the same gene; a shared finding may prompt another donor or IVF with embryo testing.
- Older reports may reflect smaller panels or older methods; ask whether stored samples can be retested if the original test used genotyping instead of sequencing.
- ASRM recommends donor screening for cystic fibrosis, spinal muscular atrophy, and hemoglobinopathies; federal rules require infectious disease checks, not genetic screening.
Table of Contents
- Which tests donor programs commonly run and what each test detects
- How a donor’s genetic results can change your family-planning options
- How to read a donor genetic report and understand residual risk
- Checklist: documents to request from the donor program and specific questions to ask
- Process, timing, and typical cost drivers for donor genetic testing and downstream options
- Life IVF Center’s approach to coordinating donor genetic testing and next steps
- Newer sequencing technologies reshaping donor genetic testing
- Ethical considerations specific to sperm donor genetic testing
- Privacy and data protection standards for donor genetic information
- How genetic testing affects donor eligibility and sperm bank screening standards
- When to request updated or follow-up testing on an older donor report
- What the research actually supports, and where common advice falls short
- Review your donor’s genetic report with our team
- FAQ
- Sources
Which tests donor programs commonly run and what each test detects
Sperm banks and fertility clinics rely on a handful of core genetic tests, but the depth of screening varies considerably from one program to the next. Understanding what each test actually measures matters more than trusting a donor’s profile badge that says “genetically tested.”
Carrier screening looks for recessive gene variants that cause no symptoms in the donor but could cause disease if a recipient also carries a variant in the same gene. Targeted carrier screening checks a short list of conditions, often based on ethnicity or family history, while expanded carrier screening (ECS) checks hundreds of genes at once regardless of ancestry. The ACOG committee opinion on carrier screening notes that expanded panels commonly range from a handful of genes to several hundred conditions depending on the laboratory and test chosen, and that broader screening increases detection but requires counseling about the risk that remains after a negative result.
ASRM’s practice guidance on gamete and embryo donation recommends that all gamete donors be screened for cystic fibrosis, spinal muscular atrophy, and hemoglobinopathies such as sickle cell disease and thalassemia, and supports pan-ethnic expanded screening when appropriate. Many programs also consider fragile X syndrome screening, particularly relevant on the egg donor side but sometimes included in broader donor panels.
Karyotype or chromosomal analysis looks at the number and structure of a donor’s chromosomes to rule out conditions like balanced translocations that can affect fertility or increase miscarriage risk in offspring. Hemoglobinopathy testing specifically checks for sickle cell trait and thalassemia traits, which are inherited in a recessive pattern similar to other carrier conditions but are tested separately in many labs.
Lab methods differ too. Some panels rely on targeted genotyping for known variants, while others use sequencing-based methods that can detect a wider range of mutations, including copy number variants (CNV) that genotyping might miss. A few practical distinctions worth asking about:
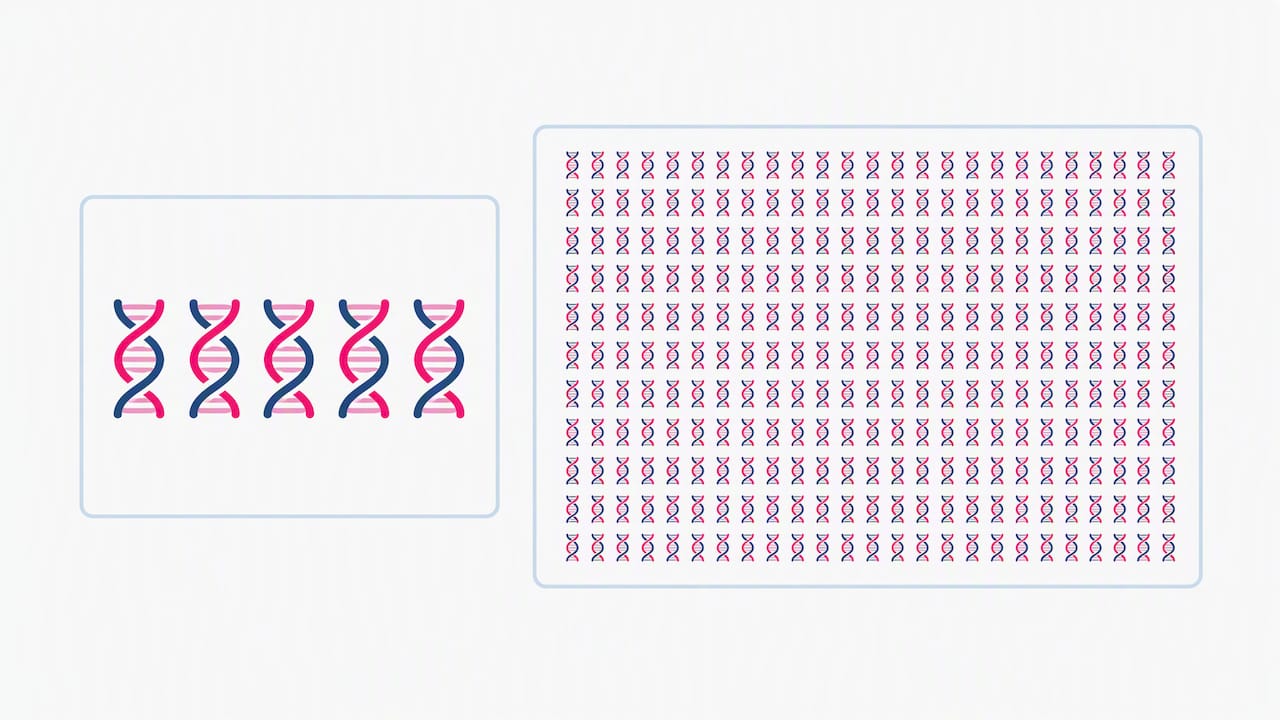
- Panel size and scope: a 5-gene panel and a 500-gene panel are both called “carrier screening,” but they catch very different things.
- Testing method: sequencing-based tests generally detect more variant types than older genotyping arrays.
- Ancestry assumptions: some labs still weight detection rates by reported ethnicity, which can miss relevant variants in donors of mixed or unknown ancestry.
- Update frequency: panels expand over time as labs add genes, so a report from several years ago may not reflect current coverage.
How a donor’s genetic results can change your family-planning options
A donor’s test results do not just sit in a file. They shape real decisions about which donor to choose, what additional testing to order, and whether to involve a reproductive endocrinologist or genetic counselor before moving forward.
- If the donor’s panel comes back negative, the main point to understand is residual risk: a negative screen lowers the chance of a carrier status for the tested conditions but does not reduce it to zero, since no panel tests every possible disease-causing variant. Continued counseling and, when relevant, recipient testing for the same conditions remain reasonable next steps.
- If the donor is identified as a carrier for a recessive condition, options include testing the intended recipient for that same gene, choosing a different donor whose panel is clear for that condition, requesting targeted testing for the specific variant if the recipient’s carrier status is already known, or pursuing IVF with preimplantation genetic testing for monogenic conditions (PGT-M) to select unaffected embryos. Prenatal diagnostic testing during a pregnancy is another option if conception has already occurred through less invasive means like IUI.
- If a donor report reveals a donor-health implication rather than a straightforward carrier finding, such as a variant linked to a treatable or late-onset adult condition, programs generally need to weigh donor eligibility and disclosure obligations to current and prospective recipients. A sperm-bank study on managing clinically relevant findings in donor applicants found that expanded carrier screening revealed clinically significant donor-health findings in a small but meaningful fraction of applicants, underscoring why pretest counseling and clear disclosure protocols matter before a donor is accepted into a program.
Each of these pathways carries different cost and timing implications. A donor swap is usually the fastest and least expensive route when another donor with compatible results is available. PGT-M adds laboratory costs and extends an IVF cycle timeline, since embryos need biopsy and genetic analysis before transfer. Genetic counseling sessions, whether to interpret a single discordant result or to plan a full reproductive strategy, typically add a separate professional fee on top of testing costs.
Pro Tip: Ask your clinic or donor program whether the donor and recipient panels test for the same genes using comparable methods before assuming a “both tested negative” result means you are in the clear.
How to read a donor genetic report and understand residual risk
A donor genetic report is only useful if you understand what the terms inside it mean. Most labs classify each variant found using a standard five-tier system: pathogenic, likely pathogenic, variant of uncertain significance (VUS), likely benign, and benign.
- Pathogenic or likely pathogenic variants are those a lab considers disease-causing; these carry the most direct relevance to reproductive planning.
- A VUS is a genetic change the lab cannot yet classify as harmful or harmless, so it typically should not drive a donor selection decision on its own without genetic counseling input.
- Benign and likely benign variants are not expected to cause disease and generally do not change reproductive risk assessment.
Panel content and testing methodology matter more than a headline gene count. A 300-gene panel that uses older genotyping methods may actually detect fewer clinically relevant variants than a 200-gene panel using full sequencing, because sequencing catches a broader range of mutation types, including structural ones that genotyping can miss.
A negative screen is reassurance, not a guarantee. ACOG’s guidance on carrier screening explains that carrier screening is meant for reproductive risk assessment rather than diagnosis, and that a negative result lowers but does not eliminate the chance of a condition, since no panel captures every disease-causing variant in every gene. ACMG’s practice resource on carrier screening adds that targeted testing remains appropriate when a specific family history exists, even if a broader panel came back clear.
This is the point where a genetic counselor earns their fee. Bring the donor’s full report, your own carrier screening results if you have them, and any known family history of inherited conditions to the appointment. A counselor can flag discordant panels, explain what a VUS means for your specific situation, and recommend whether additional targeted testing makes sense before you commit to a donor or move forward with treatment.
Checklist: documents to request from the donor program and specific questions to ask
Before choosing a donor, request a specific set of documents and ask direct questions rather than relying on a program’s summary profile page.
Documents to request:
- The full donor genetic report, not just a pass or fail summary.
- The lab name and its accreditation status, such as CLIA certification or CAP accreditation.
- The complete gene list tested and the methodology used (genotyping versus sequencing, and whether CNV analysis was included).
- The date the testing was performed.
- A summary of the donor’s reported ancestry and family medical history.
- The program’s written policy on recontacting donors or updating results if testing methods change.
Questions to ask directly:
- Can stored samples be retested if a newer, more comprehensive panel becomes available?
- Do the donor’s and the intended recipient’s carrier panels test for the same genes using comparable methods?
- Is a genetic counselor available for consultation both before donor selection and after results are reviewed?
- Who is responsible for the cost of any follow-up testing the results suggest?
If a program cannot produce the lab name, the specific gene list, or the testing date, treat that as a gap to resolve before proceeding, not a detail to skip. Verifying CLIA or CAP accreditation is usually a quick call to the lab itself, and a program unwilling to share that information is worth questioning further.
Process, timing, and typical cost drivers for donor genetic testing and downstream options
Donor genetic testing does not happen in isolation. It fits into a broader timeline that also includes infectious-disease screening and, for fresh or certain donor arrangements, mandatory quarantine periods.
FDA donor eligibility guidance requires infectious-disease testing and quarantine or retest windows for donor semen, though genetic screening itself is standard practice at most programs rather than a requirement under the same federal provisions. In practice, this means a donor’s infectious-disease clearance and quarantine period often run on a separate timeline from the genetic panel, and both need to be confirmed before a sample is released for use.
Cost drivers worth planning around:
- Expanded carrier screening panel fees, which vary by lab and the number of genes tested.
- Recipient carrier testing, needed to confirm whether your results overlap with the donor’s.
- Genetic counseling sessions, typically billed separately from the lab testing itself.
- IVF with PGT-M, if a known carrier match requires embryo selection rather than a donor swap.
At Life IVF Center, Carrier Screening for Genetic Disease is listed at $349 as a standalone test, which gives a useful reference point for what recipient-side carrier screening can cost independent of donor program fees. Billing arrangements vary: some donor programs include basic genetic screening in the donor’s listed fee, while expanded panels, recipient testing, and any counseling sessions are typically billed separately. Confirming exactly what is bundled before selecting a donor avoids surprises later in the process.
Life IVF Center’s approach to coordinating donor genetic testing and next steps
Reviewing a donor’s genetic report in isolation rarely answers the real question, which is whether that report lines up with your own results and your family-building plan. Our team reviews the donor report you bring in, compares it against recipient carrier screening when available, and flags any genes where panels differ or coverage is incomplete.
When a discordant result or a donor-health finding comes up, we coordinate next steps directly: that might mean recommending targeted follow-up testing, connecting you with genetic counseling, or discussing whether a donor swap, IUI, or IVF with PGT-M fits your situation better. This individualized review is part of how we apply our Precision IVF® framework, built around each patient’s own biology, history, and goals rather than a one-size-fits-all protocol.
If you already have a donor report in hand, our genetic testing and care coordination page outlines how we fit report review and follow-up testing into a broader treatment plan.
Newer sequencing technologies reshaping donor genetic testing
Next-generation sequencing (NGS) has become the backbone of most expanded carrier screening panels used on sperm donors today, replacing older genotyping arrays that could only detect a pre-selected list of known variants. NGS reads through large stretches of DNA directly, which means it can catch previously undocumented variants in addition to the common ones a genotyping array was built to find.
Whole genome sequencing (WGS) goes further still, reading a donor’s entire genetic code rather than a targeted panel of genes. WGS is not yet standard practice across most donor programs, partly because of cost and partly because interpreting the sheer volume of data it produces, including many variants of uncertain significance, adds complexity rather than clarity for most reproductive decisions.
Copy number variant (CNV) analysis, often bundled into modern sequencing-based panels, detects structural changes such as missing or duplicated gene segments that older single-variant genotyping could miss entirely. This matters because some inherited conditions are caused by these structural changes rather than single-letter DNA changes.
The practical takeaway for intended parents is that two donors tested a few years apart may have been screened with meaningfully different technology, even if both reports say “carrier screening performed.” Asking which method a program used, rather than just how many genes were tested, gives a clearer picture of what the donor’s clear result actually rules out.
Ethical considerations specific to sperm donor genetic testing
Expanded genetic testing does more than screen for disease risk. It also reshapes how donors are selected, which raises questions that donor programs and intended parents both need to sit with.
Broader testing can function as a form of selection beyond disease prevention, since detailed genetic information sometimes touches on traits or predispositions that go beyond straightforward inherited conditions. Bioethics literature on expanded carrier screening in gamete donation describes this shift as a new form of reproductive genetic selection, one that carries implications for donor privacy, informed consent, and how selection criteria get applied in practice.
Donors themselves need informed consent that explains what testing will reveal, including findings that may affect their own health knowledge, not just their eligibility to donate. When a donor-health finding surfaces, as happens in a small but real share of applicants, programs face a genuine tension between a donor’s privacy and a recipient’s right to know information relevant to a future child’s health.
For intended parents, the ethical weight sits closer to proportionality: deciding how much genetic information is actually useful to request, and recognizing that more testing produces more data but also more uncertainty, particularly around variants of uncertain significance that can create anxiety without changing a clinical decision. Working through these questions with a genetic counselor, rather than alone, tends to lead to more grounded decisions.
Privacy and data protection standards for donor genetic information
Genetic data is identifying in ways that most other medical information is not, and that reality shapes how donor genetic information should be handled.
A donor’s genetic report typically moves through several hands: the testing lab, the donor program, and the clinic coordinating care for the intended parents. Each handoff is a point where consent and data-handling practices matter. Asking a donor program directly about its data retention policy, who has access to results, and whether information is shared with any third parties is a reasonable step before selecting a donor.
Consumer DNA databases add a layer of complexity that donor programs could not fully anticipate when direct-to-consumer ancestry testing was less common. Bioethics research on expanded carrier screening in gamete donation notes that genetic privacy has become an active concern because consumer ancestry testing can identify donors and donor-conceived offspring unexpectedly, which means informed consent discussions should address identifiably and the possibility of future contact, not just disease risk.
For intended parents, this means thinking ahead about how a donor-conceived child’s own genetic information might surface later, whether through a clinical follow-up test or a personal ancestry search, and discussing those possibilities with a genetic counselor before testing begins rather than after a result changes the conversation.
How genetic testing affects donor eligibility and sperm bank screening standards
Genetic testing results can determine whether a donor is accepted into a program at all, separate from the infectious-disease testing that federal rules require.
FDA donor eligibility guidance sets federal requirements for infectious-disease testing and quarantine periods for donor semen, but genetic screening for inherited conditions is not mandated under those same provisions. Instead, genetic screening practices are shaped largely by professional guidance from organizations like ASRM and by each program’s own internal standards, which means coverage and rigor can vary from one sperm bank to another.
When a donor’s expanded carrier screening reveals a significant finding, whether a carrier status for a serious recessive condition or a donor-health implication, programs generally need a clear protocol for whether that donor remains eligible and how results get disclosed to recipients already using that donor’s samples. The sperm-bank study on managing ECS findings that identified clinically significant findings in about 1 in 51 applicants specifically recommends pretest counseling and clear disclosure pathways as part of responsible program design.
For intended parents, this translates into a practical takeaway: a donor’s acceptance into a program is not a guarantee of comprehensive genetic clearance, since eligibility standards differ by program and are not uniformly regulated the way infectious-disease testing is.
When to request updated or follow-up testing on an older donor report
Genetic testing technology moves fast enough that a donor report from several years ago may not reflect what current panels can detect.
Expanded carrier screening panels have grown substantially over time as labs add newly characterized genes and adopt sequencing methods that catch variant types older genotyping missed. A donor tested five or more years ago may have been screened on a panel a fraction of the size of what is standard today, even if the report still says “expanded carrier screening, negative.”
If you are considering a donor whose genetic testing is several years old, a few points are worth raising with the program directly: whether the donor’s stored samples can be retested on a current panel, whether the original lab is still operating and can confirm its methodology from that testing date, and whether the program has any policy requiring periodic retesting for donors who remain active in their catalog.
There is no single universal cutoff for when a report becomes “too old,” since that depends on which panel was originally used and how much screening technology has advanced since. A genetic counselor or your clinic can help assess whether a specific older report still provides meaningful reassurance or whether requesting updated testing makes sense before moving forward with that donor.
What the research actually supports, and where common advice falls short
The most common mistake intended parents make with donor genetic testing is treating a “negative” result as a clearance stamp rather than a probability statement. A clean panel narrows risk; it does not remove it, and the gap between those two ideas is where most disappointment and confusion later comes from.
Conventional advice tends to fixate on gene counts, as though a 500-gene panel is automatically better than a 200-gene one. What actually matters more is whether the donor’s and recipient’s panels test the same genes using comparable methods, and whether the lab’s methodology can detect the variant types relevant to your family history. A smaller, well-matched panel interpreted by someone qualified beats a large, mismatched one every time.
If there is one priority worth acting on first, it is this: get the donor’s actual report, not the program’s summary page, and have it reviewed alongside your own results before you commit. That single step resolves more uncertainty than any amount of panel-size comparison.
— Ben
Review your donor’s genetic report with our team
Choosing a donor should not mean interpreting a lab report on your own. The donor genetic report you bring can be reviewed alongside recipient carrier screening results, with an explanation of discordant findings provided within an individualized Precision IVF® framework.
Here is what that consultation covers:
- A side-by-side review of donor and recipient carrier screening results.
- Guidance on whether targeted follow-up testing or genetic counseling makes sense for your situation.
- A discussion of pathways, including IUI, IVF with PGT-M, or selecting a different donor, based on what the results actually show.
If you are weighing a donor’s genetic report right now, our genetic testing and care coordination page explains how we fold that review into your broader treatment plan, and you can also view current pricing for carrier screening and related pre-IVF testing to plan your budget. Ready to talk it through? You can book a consultation with our team directly.
This article is general information, not a substitute for advice from a qualified doctor. Consult a qualified healthcare professional about your own circumstances before acting on anything here.
FAQ
Is sperm donor genetic testing necessary before choosing a donor?
Genetic testing is not legally required for sperm donors the way infectious-disease screening is under FDA donor eligibility rules, but it is standard practice at most reputable programs and strongly supported by ASRM guidance. Skipping it means missing information that could meaningfully change your reproductive planning.
Will my baby look like my husband if I use donor sperm?
A child conceived with donor sperm inherits genetic traits, including physical features, from the sperm donor rather than from your husband, since physical resemblance follows genetic contribution. Many intended parents select donors with physical characteristics similar to their partner’s, though resemblance cannot be guaranteed from a donor profile alone; a partner resource on how genes shape a baby’s traits covers this in more depth.
Do sperm donors know if they have children from their donations?
Whether a donor learns about resulting children depends entirely on the program’s disclosure policy and the donor’s chosen anonymity status at the time of donation, not on genetic testing itself. Some programs offer identity-release arrangements while others maintain anonymity, and policies vary by program rather than following a single standard.
What should I do if my donor’s genetic testing report is several years old?
Ask the program whether the donor’s stored sample can be retested on a current expanded panel, since screening technology and gene coverage have expanded substantially over time. If retesting is not possible, a genetic counselor can help assess how much reassurance the original report still provides given the methodology available at the time it was run.
What happens if a sperm donor tests positive as a carrier for a genetic condition?
A positive carrier result does not automatically disqualify a donor, but it does mean you should request recipient testing for that same gene before proceeding. If both you and the donor carry the same recessive condition, options include selecting a different donor, pursuing IVF with PGT-M, or discussing prenatal diagnostic testing with a genetic counselor.
Sources
- ASRM practice guidance: Gamete and embryo donation
- ACOG committee opinion: Carrier screening in the age of genomic medicine
- Management considerations for clinically relevant findings on expanded carrier screening in a sperm donor applicant population
- ACMG practice resource: Screening for autosomal recessive and X-linked conditions during pregnancy and preconception
- FDA guidance: Donor eligibility and testing for reproductive cells and tissues
This article is for general educational purposes only and is not a substitute for personalized medical advice, diagnosis, or treatment. Fertility care is highly individual; please consult a qualified healthcare professional about your specific circumstances.
