Yes: carrier screening before IVF is recommended for anyone starting fertility treatment, because it reveals whether you or your partner carry gene variants that could cause serious conditions in a child. Testing before conception (rather than during pregnancy) gives you time to act on the results with options like IVF combined with PGT-M, donor gametes, or prenatal diagnosis. The immediate next step is simple: ask your clinic to schedule genetic counseling alongside your carrier screening order.
TL;DR:
- Expanded carrier screening detects more at-risk couples than ethnicity-based panels, especially in mixed or unreported ancestries, though it can produce uncertain results that require counseling.
- Preconception testing allows for sequential partner screening, confirmatory follow-up, and planning for PGT-M, all of which are limited once pregnancy is established.
- Screening results categorized as carrier couple or VUS significantly influence reproductive options, with carrier couples facing a 25 percent risk of affected children without intervention.
- Conducting carrier screening early in the IVF timeline ensures results inform treatment strategies like PGT-M, donor gametes, or prenatal testing before embryo or egg retrieval.
- Costs typically range around $349 for the test, and coordinated counseling and testing timing are crucial to integrate screening seamlessly into IVF planning.
Table of Contents
- What Carrier Screening Actually Tests For
- Why Screening Before IVF Beats Waiting Until Pregnancy
- Ethnicity-Based, Pan-Ethnic, or Expanded: Choosing a Panel
- Reading Your Results: Carrier, Carrier Couple, or VUS
- How Carrier Screening Fits Into Your IVF Timeline
- What Professional Guidelines Say, and Where Screening Falls Short
- The Life IVF Center Approach to Carrier Screening
- Ready to Talk Through Your Results With a Genetics-Informed Team?
- Sources
- FAQ
What Carrier Screening Actually Tests For
A carrier is someone who has one altered copy of a gene tied to a recessive condition but shows no symptoms themselves. Autosomal recessive conditions require two altered copies (one from each parent) to affect a child, which is why carrier status alone usually is not a health concern for the person carrying it. X-linked conditions follow a different pattern: a mother’s carrier status can affect sons more severely than daughters, because sons have only one X chromosome.
Carrier screening looks for risk. It does not diagnose disease in the person tested. Diagnostic testing, by contrast, confirms whether a fetus or embryo actually has a condition. Panels commonly screen for:
- Cystic fibrosis, an autosomal recessive lung and digestive disorder
- Spinal muscular atrophy, a neuromuscular condition affecting motor neurons
- Hemoglobinopathies such as sickle cell disease and thalassemia
- Fragile X syndrome and other X-linked conditions
Why Screening Before IVF Beats Waiting Until Pregnancy
Timing changes what you can do with the information. Testing during pregnancy narrows your options considerably; testing before conception widens them. Here is what preconception screening makes possible that prenatal-only screening does not:
- Sequential testing. You can test one partner first, and only test the second partner for the specific conditions the first partner carries, saving time and cost. If done only after conception, both partners are often tested in parallel because of time constraints, which is slower to interpret and more stressful under pressure.
- Confirmatory testing without a clock running. Positive results sometimes need follow-up testing to confirm a variant’s clinical significance, and that takes weeks you may not have once you are pregnant.
- PGT-M planning. If you and your partner are both carriers of the same recessive condition, your IVF cycle can incorporate preimplantation genetic testing for monogenic conditions to select unaffected embryos before transfer, an option that requires lead time to validate the test for your specific variant.
Ethnicity-Based, Pan-Ethnic, or Expanded: Choosing a Panel
Three approaches dominate carrier screening today, and they differ significantly in what they can find.
- Ethnicity-based screening tests for conditions more common in a specific ancestry group. It is narrower and can miss risk in people of mixed or unreported ancestry.
- Pan-ethnic screening tests everyone for the same core set of conditions (typically cystic fibrosis and spinal muscular atrophy) regardless of background.
- Expanded carrier screening (ECS) tests for dozens to hundreds of conditions at once, without relying on ancestry at all.
Expanded carrier screening identifies more at-risk couples than ethnicity-based approaches, largely because self-reported ancestry is often incomplete or inaccurate, and many conditions cross ethnic lines more than older screening models assumed. The tradeoff is interpretive complexity: broader panels turn up more variants of uncertain significance (VUS), findings where the evidence does not yet clearly show whether a variant causes disease. The National Society of Genetic Counselors and ACOG both support making ECS available to anyone considering pregnancy, paired with counseling that helps translate a dense lab report into a real decision. IVF centers using next-generation sequencing report catching pathogenic variants that older, smaller panels miss entirely, regardless of a patient’s ethnicity.
Reading Your Results: Carrier, Carrier Couple, or VUS
Most people who test end up in one of a few categories, and each points to a different next move.
- Single carrier, partner not tested or not a carrier of the same condition: low reproductive risk for that specific condition. Your clinic may still recommend partner testing for full context.
- Carrier couple (both partners carry the same recessive gene variant): each pregnancy carries a 25 percent chance of an affected child. This is the scenario where reproductive planning matters most.
- Variant of uncertain significance (VUS): the lab found something, but the science cannot yet say whether it causes disease. VUS findings generally should not drive major reproductive decisions on their own, and often warrant confirmatory or family testing before anyone treats the result as actionable.
If you and your partner learn you are a carrier couple, the realistic paths forward include IVF with PGT-M to screen embryos before transfer, using donor eggs or sperm to sidestep the shared variant, pursuing prenatal diagnostic testing like CVS or amniocentesis during a natural or unassisted pregnancy, considering adoption, or knowingly accepting the 25 percent risk. None of these is the “right” choice in the abstract. ACOG notes that preconception timing is what makes weighing these options possible rather than rushed.
Pro Tip: Bring your family medical history to your first genetics conversation, not just your test results. A cousin’s undiagnosed condition or a grandparent’s early death can sometimes point a genetic counselor toward a variant a standard panel might otherwise flag as uncertain.
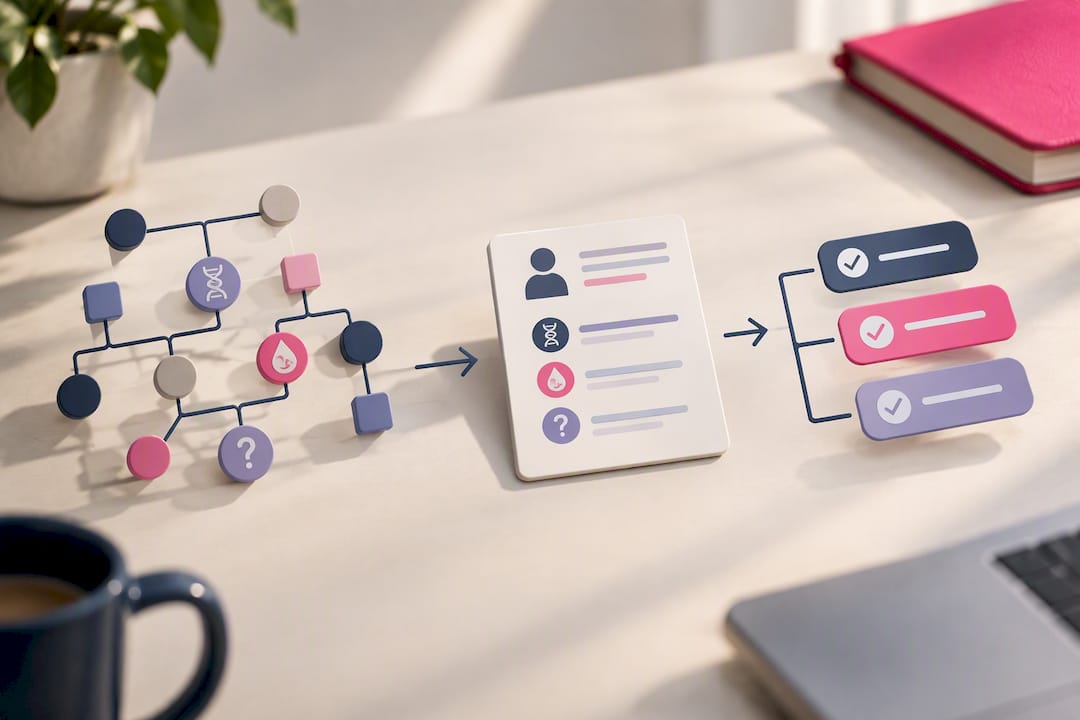
How Carrier Screening Fits Into Your IVF Timeline
Carrier screening usually happens early, well before your stimulation protocol is finalized, and the logistics are straightforward.
- Ordering. Your fertility clinic or a genetics team orders the panel, typically from a saliva or blood sample. No fasting or special preparation is required.
- Turnaround. Results generally take two to three weeks, though expanded panels covering more genes can take longer, especially if a positive result triggers confirmatory testing.
- Timing relative to IVF. Ideally, screening happens before ovarian stimulation begins, so that if PGT-M is warranted, the lab has time to build and validate a variant-specific test before your eggs are retrieved and embryos are created.
- Documentation. Bring prior genetic test results, known family conditions, and both partners’ ancestry information to your consult. It speeds interpretation and avoids redundant testing.
Cost and insurance coverage vary widely by carrier, panel size, and state mandate. Life IVF Center lists Carrier Screening for Genetic Disease at $349 as a one-time cost, which patients can compare against their own insurance benefits before deciding how to proceed. Keep a copy of every result. You will likely need it again if you pursue PGT-M or genetic counseling with a different provider later.
What Professional Guidelines Say, and Where Screening Falls Short
Major medical societies converge on a consistent message: screening before pregnancy is preferable to screening during it, and expanded panels deserve a place alongside older ethnicity-based models rather than replacing shared decision-making. ACOG recommends offering cystic fibrosis and spinal muscular atrophy screening to everyone considering pregnancy, regardless of which broader panel is chosen. The American Society for Reproductive Medicine treats PGT-M as an option to discuss case by case, not a default step for every IVF cycle.
Panel design differs meaningfully from one lab to another. Two people tested on different expanded panels can get genuinely different information, and that heterogeneity is exactly why pre- and post-test genetic counseling matters: a counselor can explain what your specific panel does and does not cover, and what a given result actually changes about your plan.
Not every gene on an expanded panel is equally well understood, and not every positive result changes clinical management in a meaningful way. Informed consent before testing, and a clear conversation about what a result will and will not tell you, should happen before the blood draw, not after.
The Life IVF Center Approach to Carrier Screening
Life IVF Center coordinates carrier screening as a standard part of pre-IVF planning, not an afterthought tacked on after stimulation starts. Our team helps schedule the test, connects patients with genetic counseling for result interpretation, and builds a PGT-M plan into the IVF cycle when a carrier couple result calls for it. Because Precision IVF® customizes protocols to each patient’s biology and history, testing and treatment timelines get built around your actual genetic results rather than a fixed template. At your consult, bring your family history and any prior test results, and we will map out whether PGT-M, donor gametes, or standard IVF is the right fit for your situation.
— Ben
Ready to Talk Through Your Results With a Genetics-Informed Team?
Carrier screening is integrated into pre-IVF planning rather than treated as a separate step between labs and clinics. That matters because a result that arrives disconnected from your IVF team often means delays while someone else interprets it after the fact.
Carrier Screening for Genetic Disease is listed at $349 as part of Life IVF Center’s pre-IVF testing menu, alongside other pre-cycle workups like infectious disease panels and karyotype analysis, so you can see the full pre-IVF picture in one place rather than piecing it together from different labs. Before your consult, gather any prior genetic test results, a two-generation family medical history, and a list of known conditions on either side of the family. Ask about scheduling genetic counseling during the same visit so results and next steps get discussed together, not in a follow-up call weeks later. If a carrier couple result points toward PGT-M or another treatment package, our team will walk you through how that fits into your specific IVF plan. Start by booking a consultation to get your questions answered directly.
This article is general information, not a substitute for advice from a qualified doctor. Consult a qualified healthcare professional about your own circumstances before acting on anything here.
Sources
- Expanded carrier screening for reproductive risk assessment: An evidence‐based practice guideline from the National Society of Genetic Counselors
- Indications and management of preimplantation genetic testing for monogenic conditions, ASRM (2023)
FAQ
What disqualifies you from doing IVF?
Carrier screening results themselves rarely disqualify anyone from IVF. A positive result changes the plan, often toward PGT-M, donor gametes, or additional counseling, rather than ruling treatment out entirely.
How common is it to have a positive result on carrier screening?
Carrier rates vary widely by condition and by which panel is used. Expanded carrier screening consistently identifies more carriers and more at-risk couples than older ethnicity-based screening, partly because it does not depend on accurate ancestry reporting.
What tests are done before starting IVF?
Beyond carrier screening, most pre-IVF workups include an infectious disease panel, semen analysis, and karyotype chromosomal analysis. Life IVF Center lists these individually, including karyotype analysis at $595 and carrier screening at $349, so patients can see itemized pre-cycle testing costs.
Is carrier screening the same as NIPT?
No. Carrier screening looks at the parents’ genes to assess the risk of passing on a recessive condition, while noninvasive prenatal testing (NIPT) screens a pregnancy for chromosomal differences in the fetus itself. They answer different questions and are typically used at different stages of family planning.
This article is for general educational purposes only and is not a substitute for personalized medical advice, diagnosis, or treatment. Fertility care is highly individual; please consult a qualified healthcare professional about your specific circumstances.
